Loading
institutionsInstitution

Dana-Farber Brigham Cancer Center
Where chemotherapy began (Farber, 1948) and where much of modern breast, lung, and myeloma oncology was defined.
Overview
Dana-Farber Brigham Cancer Center in Boston is where chemotherapy began, with Farber's aminopterin remissions in 1948, and through Dana-Farber/Harvard Cancer Center it is the largest NCI-designated centre by grant funding and fifteenth in the Newsweek/Statista oncology list. Its firsts include the discovery of EGFR mutations in lung cancer by Jänne and Johnson, KEYNOTE-522 leadership by Tolaney with Schmid in triple-negative breast cancer, Anderson's myeloma drug development and the Profile genomic testing programme. OnCo links it to BWEL and RASolute 302, to pathology foundation models from the Mahmood and Yu labs, to the Cancer Dependency Map and clonal haematopoiesis papers, and to people including Paul G. Richardson, Benjamin L. Ebert and Ann H. Partridge. Data silos are the bottleneck OnCo records against it. Its breast, lung, myeloma and paediatric programmes are listed below.
Location
Boston, US
Type
cancer center · Harvard University
Website
Newsweek 2026 oncology rank
#15
NCI designation
comprehensive
OnCo score
#6 · 216 points (45 Newsweek + 15 NCI + 156 from 78 linked objects) · ranking
Research output
From OpenAlex, oncology works in the last five years (2022 to 2026, current year in progress); counted on 2026-09-24.
Matched to Dana-Farber Cancer Institute, including child institutions. 4,333 works · 74,896 citations · 65% open access · 16% clinical trials · 2% reviews.
Oncology works per year
8972022
9932023
8952024
9002025
6482026
Most works
- Sara M. Tolaney184 works
- Caron A. Jacobson172 works
- Mark Magdi Awad98 works
- Toni K. Choueiri91 works
- Ann H. Partridge87 works
- Paolo Tarantino87 works
- Biagio Ricciuti80 works
- F. Stephen Hodi80 works
- Brian Matthew Wolpin78 works
- Frederick Lundry Locke76 works
Most cited
- Breast oncology (KEYNOTE-522, ADCs)
- Lung cancer genomics
- Myeloma
- Paediatric oncology
Alan D. D'Andrea
Director, Susan F. Smith Center for Women's Cancers and Center for DNA Damage and Repair, Dana-Farber Cancer Institute
DNA damage responseFanconi anaemia pathwayPARP inhibitor resistance
Mapped the Fanconi anaemia/BRCA DNA repair pathway and how tumours become resistant to PARP inhibitors.
Andrew J. Wagner
Sarcoma medical oncologist, Dana-Farber Cancer Institute
PEComamTOR inhibitorsRare sarcomas
Boston sarcoma doctor who first showed that mTOR inhibitors shrink perivascular epithelioid cell tumours and then led AMPECT, the trial that made nab-sirolimus the first approved treatment for these rare cancers.
Ann H. Partridge
Vice Chair of Medical Oncology; Director, Program for Young Adults with Breast Cancer
Young women's breast cancerSurvivorshipFertility after cancer
Ann Partridge led the POSITIVE trial showing women can safely pause hormone therapy to have a baby.
Anthony V. D'Amico
Professor of Radiation Oncology, Brigham and Women's Hospital and Dana-Farber Cancer Institute
Prostate radiotherapyRisk stratificationAndrogen deprivation with radiotherapy
Created the low, intermediate and high-risk classification that every prostate cancer decision starts from.
Benjamin L. Ebert
President and Chief Executive Officer
Myeloid malignanciesClonal haematopoiesisMolecular glue degraders
Discovered how lenalidomide works, launching the field of molecular-glue degraders, and defined clonal haematopoiesis before leading Dana-Farber.
Billy Starr
Founder of the Pan-Mass Challenge, which has raised $1.125 billion for Dana-Farber
Cancer fundraisingEndurance eventsMelanoma
After his mother died of melanoma he organised a bike ride across Massachusetts in 1980 with 36 riders; the Pan-Mass Challenge has since raised $1.125 billion for Dana-Farber and passes on every rider-raised dollar.
Caron A. Jacobson
Lymphoma specialist and medical director of immune effector cell therapy, Dana-Farber Cancer Institute
CAR-T cell therapyFollicular lymphomaLarge B-cell lymphoma
Boston lymphoma doctor who led ZUMA-5, the trial that brought the CAR-T therapy axicabtagene ciloleucel to relapsed follicular lymphoma.
Catherine J. Wu
Chief, Division of Stem Cell Transplantation and Cellular Therapies, Dana-Farber Cancer Institute; Professor, Harvard Medical School
Neoantigen vaccinesCancer genomicsCLL evolution
Led the first personalised neoantigen peptide vaccine trial in melanoma and mapped how CLL evolves under treatment.
Einar "Jimmy" Gustafson
The boy behind the Jimmy Fund
Paediatric lymphomaCancer fundraisingChildhood cancer
A 12-year-old lymphoma patient of Sidney Farber whose 1948 radio broadcast launched the Jimmy Fund, which has funded Dana-Farber for more than 75 years.
Eliezer M. Van Allen
Chief, Division of Population Sciences; Associate Member, Broad Institute
Computational oncologyCancer genomicsPrecision medicine
Computational oncologist who built open tools for interpreting tumour genomes and predicting response.
Elizabeth A. Mittendorf
Director, Breast Immuno-Oncology Program, Dana-Farber Brigham Cancer Center
Breast surgical oncologyImmunotherapyNeoadjuvant trials
Surgeon-scientist who led IMpassion031 and studies of surgery de-escalation after neoadjuvant immunotherapy.

Emil "Tom" Frei III
Pioneer of combination chemotherapy; long-time physician-in-chief of Dana-Farber
Combination chemotherapyAcute leukaemiaHodgkin lymphoma
With Emil Freireich he showed that combinations of drugs could cure childhood leukaemia, then extended the idea to Hodgkin lymphoma and to adjuvant treatment after surgery.
Eric P. Winer
Director, Yale Cancer Center; President and Physician-in-Chief, Smilow Cancer Hospital; Deputy Dean for Cancer Research, Yale School of Medicine
Breast cancerHER2-positive breast cancerClinical trial design
Breast cancer specialist who leads Yale Cancer Center and Smilow Cancer Hospital, and who previously ran breast oncology at Dana-Farber for more than two decades.
F. Stephen Hodi
Director, Melanoma Center and Center for Immuno-Oncology
MelanomaCheckpoint inhibitorsImmuno-oncology
First author of the 2010 ipilimumab trial that proved immunotherapy could extend survival in melanoma.
George D. Demetri
Director, Sarcoma Center and Center for Sarcoma and Bone Oncology, Dana-Farber Cancer Institute; Professor, Harvard Medical School
Gastrointestinal stromal tumourSarcomaKinase inhibitors
Led the imatinib trial in GIST that proved a targeted drug could melt away a solid tumour, and every GIST kinase inhibitor since.
Gordon J. Freeman
Professor of Medicine, Dana-Farber Cancer Institute and Harvard Medical School
PD-1/PD-L1 pathwayT-cell costimulationImmune checkpoint biology
Showed that PD-L1 is the ligand for PD-1 and that the pair switches T cells off, the foundation of checkpoint immunotherapy.
Jennifer A. Chan
Clinical Director, Gastrointestinal Cancer Center, Dana-Farber Cancer Institute
Neuroendocrine tumoursTargeted therapyCooperative-group trials
Boston oncologist who led CABINET, the trial that showed cabozantinib delays progression of advanced neuroendocrine tumours after other treatments have failed.
Jennifer R. Brown
Director, CLL Center, Dana-Farber Cancer Institute; Worthington and Margaret Collette Professor of Medicine, Harvard Medical School
Chronic lymphocytic leukaemiaBTK inhibitorsCLL genetics
Led ALPINE, the first head-to-head trial in which a next-generation BTK inhibitor (zanubrutinib) beat ibrutinib.
Joaquim Bellmunt
Director, Bladder Cancer Center, Dana-Farber Cancer Institute; Associate Professor, Harvard Medical School
Urothelial cancerImmunotherapyChemotherapy
Led KEYNOTE-045, the first trial to show immunotherapy beats chemotherapy in advanced bladder cancer.
Judy E. Garber
Chief, Division of Cancer Genetics and Prevention; Susan F. Smith Chair
Hereditary cancerBRCA1/2Cancer prevention
A leading authority on inherited cancer risk and how BRCA carriers should be treated and screened.
Kenneth C. Anderson
Kraft Family Professor of Medicine; Director, Jerome Lipper Multiple Myeloma Center
Multiple myelomaProteasome inhibitorsImmunomodulatory drugs
Translated bortezomib and lenalidomide from bench to bedside, helping turn myeloma from a two-year to a decade-plus disease.
Nancy U. Lin
Director, Metastatic Breast Cancer Program; Associate Chief, Division of Breast Oncology
Breast cancer brain metastasesHER2-positive breast cancerCNS pharmacology
Nancy Lin is the leading authority on brain metastases from breast cancer, including the HER2CLIMB tucatinib data in patients with active brain disease.
Nikhil C. Munshi
Director of Basic and Correlative Science, Jerome Lipper Multiple Myeloma Center, Dana-Farber Cancer Institute
Multiple myelomaCAR T-cell therapyMyeloma genomics
Led KarMMa, which brought idecabtagene vicleucel, the first CAR-T for myeloma, to approval.
Pasi A. Jänne
Director, Lowe Center for Thoracic Oncology; Director, Belfer Center for Applied Cancer Science
EGFR-mutant lung cancerTargeted therapy resistanceKRAS G12C
Co-discovered EGFR mutations in lung cancer and has led the drug development that followed, from osimertinib to KRAS G12C inhibitors.
Patrick Y. Wen
Director, Center for Neuro-Oncology, Dana-Farber Cancer Institute; Professor of Neurology, Harvard Medical School
Neuro-oncologyGlioblastomaResponse assessment
Neuro-oncologist who created the RANO response criteria used in every brain tumour trial and leads glioblastoma drug development.
Paul G. Richardson
Clinical Program Leader and Director of Clinical Research, Jerome Lipper Multiple Myeloma Center
Multiple myelomaNovel agentsTransplant-deferral strategies
Led the DETERMINATION trial and many of the myeloma drug approvals of the past two decades.
Philippe Armand
Lymphoma specialist, Dana-Farber Cancer Institute
Hodgkin lymphomaPrimary mediastinal B-cell lymphomaCheckpoint inhibitors in lymphoma
Boston lymphoma doctor who led KEYNOTE-170, the trial that showed pembrolizumab can control relapsed primary mediastinal B-cell lymphoma, and who helped bring PD-1 blockade to Hodgkin lymphoma.
Ravindra Uppaluri
Chief of Otolaryngology-Head and Neck Surgery, Brigham and Women's Hospital and Dana-Farber Cancer Institute
Head and neck surgeryNeoadjuvant immunotherapyTumour immunology
Surgeon-scientist who led the first neoadjuvant pembrolizumab trial in head and neck cancer and the KEYNOTE-689 study that made it standard.

Richard M. Stone
Chief of Staff and Director of Translational Research, Adult Leukemia Program, Dana-Farber Cancer Institute
Acute myeloid leukaemiaFLT3 inhibitorsCooperative-group trials
Led RATIFY, the trial that made midostaurin the first targeted therapy added to induction chemotherapy for AML.
Robert Sandler
Child whose remission on aminopterin in 1947 was the first in leukaemia
Acute lymphoblastic leukaemiaHistory of chemotherapy
A two-year-old with acute leukaemia treated by Sidney Farber with the folate antagonist aminopterin from December 1947. His temporary remission, reported in 1948, was the first evidence that a drug could turn back leukaemia.
Sara M. Tolaney
Chief, Division of Breast Oncology; Associate Director, Susan F. Smith Center for Women's Cancers
Breast cancerHER2-positive breast cancerAntibody-drug conjugates
Leads Dana-Farber's breast oncology division and many of the trials that moved ADCs and de-escalated therapy into breast cancer care.

Sean Parker
Founder of the Parker Institute for Cancer Immunotherapy
Cancer immunotherapyResearch networksPhilanthropy
In 2016 he founded and funded an institute that runs cancer immunotherapy research as one network across a dozen leading cancer centres, sharing data, samples and patents rather than competing for them.
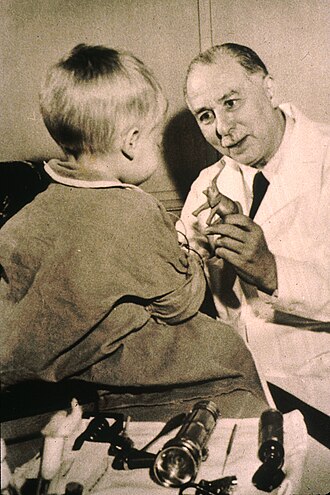
Sidney Farber
Pathologist who produced the first chemotherapy remissions in childhood leukaemia; father of modern chemotherapy
Paediatric pathologyAcute lymphoblastic leukaemiaChemotherapy
In 1947-48 he showed that the folate antagonist aminopterin could send childhood leukaemia into remission, the first drug ever to do so. He then built Dana-Farber and, with Mary Lasker, won the 1971 National Cancer Act.
Steven P. Treon
Director, Bing Center for Waldenström's Macroglobulinemia, Dana-Farber Cancer Institute
Waldenström macroglobulinaemiaMYD88 and CXCR4 genomicsBTK inhibitors
Discovered the MYD88 mutation that defines Waldenström macroglobulinaemia and led the trial that made ibrutinib its first approved drug.

Ted Williams
Boston Red Sox star who was the Jimmy Fund's public champion for half a century
Cancer fundraisingPaediatric cancerSport and philanthropy
From the 1940s until his last clinic visit in 1999 the greatest hitter in baseball raised money for Dana-Farber's Jimmy Fund and visited children on the wards on condition that no one wrote about it.

Toni K. Choueiri
Director, Lank Center for Genitourinary Oncology
Kidney cancerImmunotherapy combinationsHIF-2α
Leads kidney cancer research worldwide, including the adjuvant pembrolizumab and belzutifan trials.
Ursula A. Matulonis
Chief, Division of Gynecologic Oncology
Ovarian cancerPARP inhibitorsAntibody-drug conjugates
Ursula Matulonis led the MIRASOL trial that gave ovarian cancer its first ADC with a survival benefit.

William G. Kaelin Jr.
Sidney Farber Professor of Medicine; HHMI Investigator
VHL and HIF biologyKidney cancerOxygen sensing
William Kaelin is the Nobel laureate whose work on VHL and HIF-2α led directly to belzutifan.
observationalThe Lancet 2023343 citations
PATHFINDER: the first prospective test of a multi-cancer blood test in people without symptoms
A multi-cancer blood test can be run in ordinary clinics, and most positive results can be resolved with imaging. But six in ten positives are false alarms that take months to resolve, and the test misses most cancers. Whether it reduces late-stage cancer or deaths is unknown; that requires randomised trials.
observationalJAMA Oncology 2022335 citations
Association of high tumor mutation burden in non-small cell lung cancers with increased immune infiltration and improved clinical outcomes of PD-L1 blockade across PD-L1 expression levels
It is the strongest case that mutation burden is real biology in lung cancer and, at the same time, the clearest demonstration that its threshold is not fixed, which is why it never became a reliable selector.
observationalJournal of Thoracic Oncology 2022357 citations
Diminished efficacy of programmed death-(ligand)1 inhibition in STK11- and KEAP1-mutant lung adenocarcinoma is affected by KRAS mutation status
It corrected a widely repeated simplification. An STK11 or KEAP1 mutation is not by itself a reason to expect immunotherapy to fail; it is a reason to expect it in a KRAS-mutant tumour, which is how the result should be read on a report.
rctNew England Journal of Medicine 2021changed practice622 citations
KEYNOTE-564: a year of pembrolizumab after kidney cancer surgery
Patients whose kidney cancer has been removed but who are at high risk of recurrence (large or high-grade tumours, node involvement, or resected metastases) can now be offered a year of pembrolizumab, which increases the chance of being alive and cancer-free several years later. Roughly nine patients need treatment to prevent one recurrence at two years, and some will have permanent side effects, so shared decision-making matters. Why pembrolizumab succeeded where similar drugs failed is not fully understood.
methodsNucleic Acids Research 20204,312 citations
Li 2020: TIMER2.0 for analysis of tumour-infiltrating immune cells
TIMER2.0 is one of the most used tools in cancer immunogenomics and its multi-algorithm design is a reminder that computational immune cell estimates are model-dependent and should be cross-checked.
observationalAnnals of Oncology 2020305 citations
Prevalence and mutational determinants of high tumor mutation burden in breast cancer
TMB-high is uncommon but not negligible in TNBC, rises at relapse, and the tumour-agnostic pembrolizumab indication makes it worth measuring on a metastatic biopsy.
observationalClinical Cancer Research 2020148 citations
Tumor mutational burden and PTEN alterations as molecular correlates of response to PD-1/L1 blockade in metastatic triple-negative breast cancer
PTEN loss, the most common PI3K-pathway lesion in TNBC, may mark primary immunotherapy resistance, and TMB may add to PD-L1 in choosing who gets checkpoint blockade.
observationalGenetics in Medicine 2019183 citations
Germline cancer susceptibility gene variants, somatic second hits, and survival outcomes in patients with resected pancreatic cancer
A germline result is not the whole story: without loss of the second allele the tumour may not be repair-deficient, which is why tumour sequencing and, in trials, HRD signatures are read alongside.
16 more, oldest last
Assessment of resistance mechanisms and clinical implications in patients with EGFR T790M-positive lung cancer and acquired resistance to osimertinibAssociation of alterations in main driver genes with outcomes of patients with resected pancreatic ductal adenocarcinomaGenetic mechanisms of immune evasion in colorectal cancerMolecular subtypes of diffuse large B cell lymphoma are associated with distinct pathogenic mechanisms and outcomesReal-time genomic characterization of advanced pancreatic cancer to enable precision medicineDefining a Cancer Dependency Map: which genes each cancer cell line cannot live withoutIntegrated genomic characterization of pancreatic ductal adenocarcinomaLi 2017: TIMER, a web server for estimating immune cells in tumour genomic dataGenomic correlates of immune-cell infiltrates in colorectal carcinomaMET exon 14 mutations in non-small-cell lung cancer are associated with advanced age and stage-dependent MET genomic amplification and c-Met overexpressionJaiswal: clonal haematopoiesis, the pre-leukaemic clones in most people over 70Hodi 2010: ipilimumab, the first checkpoint inhibitor, extends survival in metastatic melanomaSites of distant recurrence and clinical outcomes in patients with metastatic triple-negative breast cancer: high incidence of central nervous system metastasesMET amplification leads to gefitinib resistance in lung cancer by activating ERBB3 signalingEGFR mutation and resistance of non-small-cell lung cancer to gefitinibEGFR mutations in lung cancer: correlation with clinical response to gefitinib therapy
Similar pages
- InstitutionBroad Institute of MIT and Harvard
Shares Break up the liquid droplets where oncogenic transcription happens, Catherine J. Wu, Let patients themselves donate their records and samples for ultra-rare cancers, Genomic correlates of immune-cell infiltrates in colorectal carcinoma.
- InstitutionMemorial Sloan Kettering Cancer Center
Shares Break Through Cancer, Damon Runyon Cancer Research Foundation, National Comprehensive Cancer Network (NCCN), Sean Parker.
- InstitutionMD Anderson Cancer Center
Shares Break Through Cancer, The V Foundation for Cancer Research, Emil "Tom" Frei III, National Comprehensive Cancer Network (NCCN).
- BottleneckFunding follows fashion, not burden
Shares Pan-Mass Challenge, Billy Starr, Einar "Jimmy" Gustafson, Ted Williams.
cancers
Bladder & urothelial cancerDiffuse large B-cell lymphomaHead and neck squamous cell carcinomaHodgkin lymphomaMultiple myelomaNeuroblastoma (paediatric)Non-small-cell lung cancerNUT carcinoma (midline carcinoma with NUTM1 rearrangement)Renal cell carcinomaSmall-cell lung cancerTriple-negative breast cancer (TNBC)
technologies
drugs
Phase 1Personalised neoantigen long-peptide vaccine with poly-ICLC adjuvant
companies
institutions
Breast Cancer Research FoundationButaro Cancer Center of ExcellenceDamon Runyon Cancer Research FoundationDavid H. Koch Institute for Integrative Cancer Research at MITHoward Hughes Medical InstituteLustgarten FoundationNational Cancer Institute (NIH)National Comprehensive Cancer Network (NCCN)Pan-Mass ChallengeParker Institute for Cancer ImmunotherapyThe Jimmy FundThe V Foundation for Cancer Research
pathways
trials
roadmaps
Lymphoma roadmap: from a jaw tumour in Uganda and the first human cancer virus to gene-expression subtypes, PET-adapted chemotherapy, CAR-T cells, bispecific antibodies and the genetics-directed trials now recruitingTriple-negative breast cancer roadmap: from a remainder defined by three negative tests to immunotherapy, antibody-drug conjugates and the residual disease problem
ideas
Break up the liquid droplets where oncogenic transcription happensImplant a tiny device that tests twenty drugs inside the patient's own tumourLet patients themselves donate their records and samples for ultra-rare cancersTrials that include, and report, brain metastases in triple-negative breast cancerWhich patients' blood clones will become leukaemia after treatment?
collections
people
Alan D. D'AndreaAndrew J. WagnerAnn H. PartridgeAnthony V. D'AmicoBenjamin L. EbertBilly StarrCaron A. JacobsonCatherine J. WuEinar "Jimmy" GustafsonEliezer M. Van AllenElizabeth A. MittendorfEmil "Tom" Frei IIIEric P. WinerF. Stephen HodiGeorge D. DemetriGordon J. FreemanJennifer A. ChanJennifer R. BrownJoaquim BellmuntJudy E. GarberKenneth C. AndersonNancy U. LinNikhil C. MunshiPasi A. JännePatrick Y. WenPaul G. RichardsonPhilippe ArmandRavindra UppaluriRichard M. StoneRobert SandlerSara M. TolaneySean ParkerSidney FarberSteven P. TreonTed WilliamsToni K. ChoueiriUrsula A. MatulonisWilliam G. Kaelin Jr.
bottlenecks
key papers
Assessment of resistance mechanisms and clinical implications in patients with EGFR T790M-positive lung cancer and acquired resistance to osimertinibAssociation of alterations in main driver genes with outcomes of patients with resected pancreatic ductal adenocarcinomaAssociation of high tumor mutation burden in non-small cell lung cancers with increased immune infiltration and improved clinical outcomes of PD-L1 blockade across PD-L1 expression levelsDefining a Cancer Dependency Map: which genes each cancer cell line cannot live withoutDiminished efficacy of programmed death-(ligand)1 inhibition in STK11- and KEAP1-mutant lung adenocarcinoma is affected by KRAS mutation statusEGFR mutation and resistance of non-small-cell lung cancer to gefitinibEGFR mutations in lung cancer: correlation with clinical response to gefitinib therapyGenetic mechanisms of immune evasion in colorectal cancerGenomic correlates of immune-cell infiltrates in colorectal carcinomaGermline cancer susceptibility gene variants, somatic second hits, and survival outcomes in patients with resected pancreatic cancerHodi 2010: ipilimumab, the first checkpoint inhibitor, extends survival in metastatic melanomaIntegrated genomic characterization of pancreatic ductal adenocarcinomaJaiswal: clonal haematopoiesis, the pre-leukaemic clones in most people over 70KEYNOTE-564: a year of pembrolizumab after kidney cancer surgeryLi 2017: TIMER, a web server for estimating immune cells in tumour genomic dataLi 2020: TIMER2.0 for analysis of tumour-infiltrating immune cellsMET amplification leads to gefitinib resistance in lung cancer by activating ERBB3 signalingMET exon 14 mutations in non-small-cell lung cancer are associated with advanced age and stage-dependent MET genomic amplification and c-Met overexpressionMolecular subtypes of diffuse large B cell lymphoma are associated with distinct pathogenic mechanisms and outcomesPATHFINDER: the first prospective test of a multi-cancer blood test in people without symptomsPrevalence and mutational determinants of high tumor mutation burden in breast cancerReal-time genomic characterization of advanced pancreatic cancer to enable precision medicineSites of distant recurrence and clinical outcomes in patients with metastatic triple-negative breast cancer: high incidence of central nervous system metastasesTumor mutational burden and PTEN alterations as molecular correlates of response to PD-1/L1 blockade in metastatic triple-negative breast cancer
Open-source projects
All open source in oncology →Open-source projects that this organisation maintains, from OnCo's own catalogue: licence and last activity as the repository reported them on the day of the fetch. Listing is not endorsement; check the licence before reuse and the validation before clinical use.
Dana-Farber's toolkit for computational pathology: preprocessing whole-slide and multiplex images and training models.
Reconstructs T-cell and B-cell receptor repertoires from bulk or single-cell RNA-seq of tumours.
The Van Allen lab's clinical interpretation algorithm and knowledge base for cancer genomics, matching variants to therapies and trials.