Loading
institutionsInstitution

Johns Hopkins Hospital / Sidney Kimmel Comprehensive Cancer Center
Johns Hopkins is the birthplace of cancer genomics (Vogelstein), MSI-high immunotherapy (Le, Diaz), and liquid biopsy and MCED science (CancerSEEK).
Overview
Johns Hopkins Hospital and its Sidney Kimmel Comprehensive Cancer Center in Baltimore are where cancer genomics began with Vogelstein and Kinzler, and the centre holds NCI comprehensive designation and tenth place in the Newsweek/Statista oncology ranking. Its record includes pembrolizumab in mismatch-repair-deficient tumours, the first tumour-agnostic approval, led by Le and Diaz, the CancerSEEK liquid biopsy that fed Exact Sciences' multi-cancer early detection programme, and the Bloomberg-Kimmel Institute for Cancer Immunotherapy under Drew M. Pardoll and Elizabeth M. Jaffee. OnCo links it to DELFI Diagnostics, to the DETECT-A, DYNAMIC and CheckMate 816 papers, and to pathways from epigenetic reprogramming to telomere maintenance. Whether blood-based early detection lowers harm as well as finding cancers is the question its own work posed. Programmes and people are listed below.
Location
Baltimore, US
Type
cancer center · Johns Hopkins University
Newsweek 2026 oncology rank
#10
NCI designation
comprehensive
OnCo score
#5 · 221 points (50 Newsweek + 15 NCI + 156 from 78 linked objects) · ranking
Research output
From OpenAlex, oncology works in the last five years (2022 to 2026, current year in progress); counted on 2026-09-24.
Matched to Johns Hopkins University, including child institutions. 2,962 works · 42,161 citations · 70% open access · 8% clinical trials · 3% reviews.
Oncology works per year
6522022
7102023
6322024
5642025
4042026
Most works
- Elizabeth M. Jaffee102 works
- Jin Peng He94 works
- Ralph H. Hruban66 works
- Richard Andrew Burkhart66 works
- Mark M. Yarchoan60 works
- Laura DeLong Wood57 works
- Patrick M. Forde57 works
- Elana Judith Fertig56 works
- Amol Kumar Narang52 works
- Julie R. Brahmer51 works
Most cited
- Cancer genomics
- MSI-H immunotherapy
- Liquid biopsy / MCED
- Bloomberg-Kimmel Immunotherapy
Amanda Nickles Fader
Gynaecologic oncologist, Johns Hopkins
Uterine serous carcinomaHER2-directed therapyMinimally invasive gynaecologic surgery
Baltimore gynaecologic oncologist who led the trial showing that adding trastuzumab to chemotherapy helps women with HER2-positive uterine serous carcinoma, an aggressive form of endometrial cancer.

Bert Vogelstein
Clayton Professor of Oncology; Co-Director, Ludwig Center; HHMI Investigator
Cancer geneticsColorectal tumorigenesisLiquid biopsy
Bert Vogelstein is the most-cited scientist in cancer genetics: he mapped how colorectal cancer develops and founded the field of cancer genome sequencing and blood-based detection.

Daniel K. Ludwig
Shipping magnate who endowed the Ludwig Institute for Cancer Research in 1971
Cancer research endowmentInstitute buildingCancer immunology
In 1971 he put nearly all of his international holdings into a cancer research institute that carries his name reluctantly; it has since spent more than $1.8 billion of its own money on cancer science.

David H. Koch
Prostate cancer patient whose gifts built the MIT Koch Institute and the MSK Koch Center for Cancer Care
Cancer research buildingsEngineering and cancer biologyProstate cancer
Treated for prostate cancer from 1992, he gave MIT $100 million in 2007 to build an institute that puts engineers and cancer biologists under one roof, and MSK $150 million in 2015 for a new outpatient cancer building.
Drew M. Pardoll
Director, Bloomberg~Kimmel Institute for Cancer Immunotherapy
Tumour immunologyPD-1 pathwayCancer vaccines
Immunologist who helped define the PD-1 pathway's role in cancer and built one of the largest immunotherapy institutes.
Dung T. Le
Professor of Oncology; Co-Director, GI Cancer Immunotherapy
MSI-high cancersPancreatic cancer immunotherapyCancer vaccines
First author of the studies that showed mismatch-repair-deficient tumours respond to PD-1 blockade regardless of origin.

Elizabeth M. Jaffee
Deputy Director, Sidney Kimmel Comprehensive Cancer Center; Co-Director, Skip Viragh Center for Pancreas Cancer
Pancreatic cancerCancer vaccinesTumour immunology
Pancreatic cancer immunologist who developed the GVAX vaccine and led national cancer policy panels.
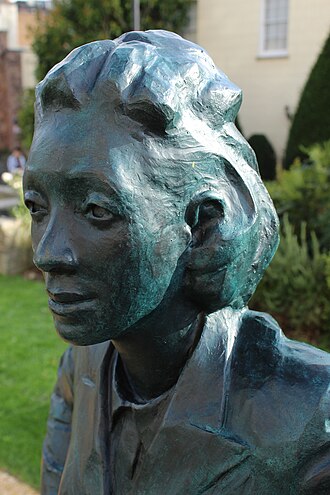
Henrietta Lacks
Patient whose cells became the HeLa line; the case that reshaped research consent
Cervical cancerResearch ethicsCell lines
Her cervical cancer cells, taken in 1951 without her knowledge, became HeLa, the first immortal human cell line. Her story changed how consent and family rights in research are handled.
Julie R. Brahmer
Director, Thoracic Oncology; Co-Director, Upper Aerodigestive Department, Bloomberg~Kimmel Institute
Lung cancer immunotherapyPD-1/PD-L1Mesothelioma
Led CheckMate 017, the first trial to show immunotherapy beats chemotherapy in lung cancer.
Kellie N. Smith
Associate Professor of Oncology; Bloomberg~Kimmel Institute
T-cell immunologyNeoantigen-specific T cellsMANAFEST assay
Developed the MANAFEST assay to track the tumour-specific T cells that immunotherapy awakens.
Kenneth W. Kinzler
Professor of Oncology; Co-Director, Ludwig Center
Cancer geneticsAPC and Wnt signallingGenome sequencing
Co-discovered APC, the gatekeeper gene of colorectal cancer, and co-led the first cancer genome sequences.

Michael Bloomberg
Johns Hopkins' largest benefactor; co-founder of the Bloomberg~Kimmel Institute for Cancer Immunotherapy
Cancer immunotherapyInstitute buildingPublic health philanthropy
In 2016 his $50 million, matched by Sidney Kimmel and others to $125 million, launched a Johns Hopkins institute that put more than a hundred scientists and clinicians to work on cancer immunotherapy.
Nickolas Papadopoulos
Professor of Oncology and Pathology, Ludwig Center and Sidney Kimmel Comprehensive Cancer Center, Johns Hopkins
Early cancer detectionLiquid biopsyCancer genetics
Co-developed CancerSEEK, the blood test that showed multi-cancer early detection is possible, and ran the first prospective screening study of it.
Patrick M. Forde
Director, Thoracic Oncology Clinical Research Program
Neoadjuvant immunotherapyLung cancerMesothelioma
Led CheckMate 816, which established neoadjuvant chemo-immunotherapy for resectable lung cancer.
Sidney Kimmel
Founder of the Sidney Kimmel Foundation for Cancer Research; namesake of the Johns Hopkins cancer centre and Jefferson's medical college
Cancer research philanthropyYoung investigator fundingCancer immunotherapy
The Jones Apparel founder has given $157 million to Johns Hopkins since 2001, which named its cancer centre for him, and put $50 million into the Bloomberg~Kimmel Institute for Cancer Immunotherapy in 2016.
Stephen B. Baylin
Virginia and D.K. Ludwig Professor of Oncology and Medicine
Cancer epigeneticsDNA methylationEpigenetic therapy
Founder of cancer epigenetics, showing that abnormal DNA methylation silences tumour-suppressor genes and can be reversed by drugs.
Suzanne L. Topalian
Bloomberg~Kimmel Professor of Cancer Immunotherapy; Associate Director, Bloomberg~Kimmel Institute
PD-1 blockadeMelanomaNeoadjuvant immunotherapy
Suzanne Topalian led the first nivolumab trials showing PD-1 blockade works across several cancers.
William G. Nelson
Director, Sidney Kimmel Comprehensive Cancer Center
Prostate cancerEpigeneticsCancer prevention
William Nelson is the long-time director of the Johns Hopkins cancer centre and a prostate cancer epigenetics researcher.
rctNew England Journal of Medicine 2022changed practice2,339 citations
CheckMate 816: three cycles of nivolumab plus chemotherapy before lung cancer surgery
Patients with operable stage II-III lung cancer without EGFR or ALK alterations should have chemo-immunotherapy discussed before surgery rather than only afterwards. Three pre-operative cycles do not compromise the operation and improve cure rates. Whether to continue immunotherapy after surgery, as the perioperative trials do, and whether patients with pCR need any further treatment, remain open questions.
rctNew England Journal of Medicine 2022changed practice765 citations
DYNAMIC: a blood test safely halved chemotherapy use after surgery for stage II colon cancer
For stage II colon cancer, where most patients are cured by surgery alone, a blood test can identify the minority who benefit from chemotherapy and spare everyone else its side effects. It does not yet prove that treating ctDNA-positive patients improves survival compared with not treating them.
observationalJournal of Clinical Oncology 2022changed practice198 citations
The Multicenter Cancer of Pancreas Screening Study: Impact on Stage and Survival
The stage shift the pancreatic cancer page quotes (about three in four surveillance-detected cancers at stage I) and the strongest argument for offering surveillance to every germline carrier found by universal testing, which the NHS does not yet do outside research.
rctJournal of Clinical Oncology 2021122 citations
TRANSFORMER: bipolar androgen therapy versus enzalutamide in asymptomatic metastatic castration-resistant prostate cancer
The first randomised evidence that the order in which prostate cancer treatments are given changes how long they work, independently of which treatments they are. It is also a rare trial in which quality of life pointed one way and the primary endpoint pointed nowhere.
observationalScience 2020513 citations
DETECT-A: a blood test plus PET-CT found treatable cancers in 10,000 women with no symptoms
A blood test can find early, treatable cancers in people who feel well, including cancers for which no screening exists. It is not a replacement for mammography or colonoscopy but a possible addition. Larger randomised trials are needed to show benefit outweighs harm.
translationalNature Communications 2020115 citations
Genomic characterization of malignant progression in neoplastic pancreatic cysts
It gives surveillance a target and a timetable: catch high-grade dysplasia and there are about three years before invasion, and TGF-beta pathway loss is the event to detect.
guidelineGut 2020changed practice472 citations
Management of patients with increased risk for familial pancreatic cancer: updated recommendations from the International Cancer of the Pancreas Screening (CAPS) Consortium
The rulebook behind the CAPS cohorts and the UK EUROPAC programme; it is also the reason surveillance for carriers is not yet a routine NHS service, because the consortium itself asked for it to stay within research until benefit was shown.
reviewNature Reviews Clinical Oncology 20201,035 citations
The tumour microenvironment in pancreatic cancer: clinical challenges and opportunities
The reference for why pancreatic microenvironment trials read as a list of failures and what the field now means by remodelling rather than removing the stroma.
35 more, oldest last
Circulating tumor DNA as a clinical test in resected pancreatic cancerDetection and localization of surgically resectable cancers with a multi-analyte blood testIPMNs with co-occurring invasive cancers: neighbours but not always relativesPrecancerous neoplastic cells can move through the pancreatic ductal systemRESTORE: bipolar androgen therapy after progression on enzalutamide in metastatic castration-resistant prostate cancerRisk of Neoplastic Progression in Individuals at High Risk for Pancreatic Cancer Undergoing Long-term SurveillanceCombined circulating tumor DNA and protein biomarker-based liquid biopsy for the earlier detection of pancreatic cancersDeleterious germline mutations in patients with apparently sporadic pancreatic adenocarcinomaLe 2017: mismatch-repair deficiency predicts response to PD-1 blockade across twelve tumour types, leading to the first tissue-agnostic drug approvalLimited heterogeneity of known driver gene mutations among the metastases of individual patients with pancreatic cancerCirculating tumor DNA analysis detects minimal residual disease and predicts recurrence in patients with stage II colon cancerWhole genome sequencing defines the genetic heterogeneity of familial pancreatic cancerA combination of molecular markers and clinical features improve the classification of pancreatic cystsA revised classification system and recommendations from the Baltimore consensus meeting for neoplastic precursor lesions in the pancreasClinical implications of genomic alterations in the tumour and circulation of pancreatic cancer patientsLe 2015: PD-1 blockade works in tumours with mismatch-repair deficiency, whatever the organAR-V7 and resistance to enzalutamide and abiraterone in prostate cancerCancer genome landscapes: about 140 driver genes, and each tumour needs only a handfulPardoll 2012: the blockade of immune checkpoints in cancer immunotherapyPresence of somatic mutations in most early-stage pancreatic intraepithelial neoplasiaThe molecular evolution of acquired resistance to targeted EGFR blockade in colorectal cancersRecurrent GNAS mutations define an unexpected pathway for pancreatic cyst developmentWhole-exome sequencing of neoplastic cysts of the pancreas reveals recurrent mutations in components of ubiquitin-dependent pathwaysDistant metastasis occurs late during the genetic evolution of pancreatic cancerDPC4 gene status of the primary carcinoma correlates with patterns of failure in patients with pancreatic cancerCore signaling pathways in human pancreatic cancers revealed by global genomic analysesPancreatic intraepithelial neoplasia: a new nomenclature and classification system for pancreatic duct lesionsVogelstein, Lane and Levine 2000: surfing the p53 networkIncidence and functional consequences of hMLH1 promoter hypermethylation in colorectal carcinomaGenetic instability in colorectal cancersInactivation of the type II TGF-beta receptor in colon cancer cells with microsatellite instabilityEl-Deiry 1993: WAF1, the gene through which p53 stops cell divisionHollstein 1991: p53 mutations in human cancersA genetic model for colorectal tumorigenesisGenetic alterations during colorectal-tumor development
Similar pages
- CancerIntraductal papillary mucinous neoplasm and other pancreatic cystic precursors
Shares Pancreatic intraepithelial neoplasia: a new nomenclature and classification system for pancreatic duct lesions, A revised classification system and recommendations from the Baltimore consensus meeting for neoplastic precursor lesions in the pancreas, Precancerous neoplastic cells can move through the pancreatic ductal system, AI that spots pancreatic cancer on scans taken a year before diagnosis.
- TechnologyHigh-risk pancreatic surveillance (CAPS / PRECEDE)
Shares Precancerous neoplastic cells can move through the pancreatic ductal system, Distant metastasis occurs late during the genetic evolution of pancreatic cancer, Whole genome sequencing defines the genetic heterogeneity of familial pancreatic cancer, Genomic characterization of malignant progression in neoplastic pancreatic cysts.
- TermCell-free DNA (cfDNA)
Shares Clinical implications of genomic alterations in the tumour and circulation of pancreatic cancer patients, Combined circulating tumor DNA and protein biomarker-based liquid biopsy for the earlier detection of pancreatic cancers, Detection and localization of surgically resectable cancers with a multi-analyte blood test, DETECT-A: a blood test plus PET-CT to screen 10,006 women with no symptoms.
- TargetSMAD4
Shares IPMNs with co-occurring invasive cancers: neighbours but not always relatives, DPC4 gene status of the primary carcinoma correlates with patterns of failure in patients with pancreatic cancer, Genomic characterization of malignant progression in neoplastic pancreatic cysts, A combination of molecular markers and clinical features improve the classification of pancreatic cysts.
- PathwayClonal evolution & minimal residual disease
Shares Limited heterogeneity of known driver gene mutations among the metastases of individual patients with pancreatic cancer, Precancerous neoplastic cells can move through the pancreatic ductal system, Distant metastasis occurs late during the genetic evolution of pancreatic cancer, IPMNs with co-occurring invasive cancers: neighbours but not always relatives.
- TargetGNAS
Shares A revised classification system and recommendations from the Baltimore consensus meeting for neoplastic precursor lesions in the pancreas, IPMNs with co-occurring invasive cancers: neighbours but not always relatives, Presence of somatic mutations in most early-stage pancreatic intraepithelial neoplasia, Recurrent GNAS mutations define an unexpected pathway for pancreatic cyst development.
- PersonLuis A. Diaz Jr.
Shares Recurrent GNAS mutations define an unexpected pathway for pancreatic cyst development, A combination of molecular markers and clinical features improve the classification of pancreatic cysts, The molecular evolution of acquired resistance to targeted EGFR blockade in colorectal cancers, Le 2017: mismatch-repair deficiency predicts response to PD-1 blockade across twelve tumour types, leading to the first tissue-agnostic drug approval.
- PathwayMismatch repair & microsatellite instability
Shares Genetic instability in colorectal cancers, Inactivation of the type II TGF-beta receptor in colon cancer cells with microsatellite instability, Incidence and functional consequences of hMLH1 promoter hypermethylation in colorectal carcinoma, Le 2017: mismatch-repair deficiency predicts response to PD-1 blockade across twelve tumour types, leading to the first tissue-agnostic drug approval.
cancers
technologies
drugs
ApprovedMonoclonal antibody (anti-PD-1)
Pembrolizumab · Keytruda / Keytruda Qlex (SC)
companies
institutions
pathways
terms
trials
roadmaps
Colorectal cancer roadmap: from the adenoma-carcinoma sequence and the first screening trials to total mesorectal excision, oxaliplatin, RAS testing, immunotherapy for mismatch repair-deficient disease, ctDNA-guided treatment and organ preservationPancreatic cancer roadmap: from Whipple's operation to gemcitabine, FOLFIRINOX, adjuvant chemotherapy, PARP inhibition, KRAS inhibition, vaccines and the surveillance question
ideas
AI that spots pancreatic cancer on scans taken a year before diagnosisBlock the recycling that keeps dormant cells aliveCheap DNA fragment-pattern blood test as a first sieve before expensive cancer testsKeep them asleep: dormancy maintenance as adjuvant therapyTake high-dose testosterone to phase 3, with progression-free survival through the second line as the primary endpoint
people
key papers
A combination of molecular markers and clinical features improve the classification of pancreatic cystsA genetic model for colorectal tumorigenesisA revised classification system and recommendations from the Baltimore consensus meeting for neoplastic precursor lesions in the pancreasAR-V7 and resistance to enzalutamide and abiraterone in prostate cancerCancer genome landscapes: about 140 driver genes, and each tumour needs only a handfulCheckMate 816: three cycles of nivolumab plus chemotherapy before lung cancer surgeryCirculating tumor DNA analysis detects minimal residual disease and predicts recurrence in patients with stage II colon cancerCirculating tumor DNA as a clinical test in resected pancreatic cancerClinical implications of genomic alterations in the tumour and circulation of pancreatic cancer patientsCombined circulating tumor DNA and protein biomarker-based liquid biopsy for the earlier detection of pancreatic cancersCore signaling pathways in human pancreatic cancers revealed by global genomic analysesDeleterious germline mutations in patients with apparently sporadic pancreatic adenocarcinomaDETECT-A: a blood test plus PET-CT found treatable cancers in 10,000 women with no symptomsDetection and localization of surgically resectable cancers with a multi-analyte blood testDistant metastasis occurs late during the genetic evolution of pancreatic cancerDPC4 gene status of the primary carcinoma correlates with patterns of failure in patients with pancreatic cancerDYNAMIC: a blood test safely halved chemotherapy use after surgery for stage II colon cancerEl-Deiry 1993: WAF1, the gene through which p53 stops cell divisionGenetic alterations during colorectal-tumor developmentGenetic instability in colorectal cancersGenomic characterization of malignant progression in neoplastic pancreatic cystsHollstein 1991: p53 mutations in human cancersInactivation of the type II TGF-beta receptor in colon cancer cells with microsatellite instabilityIncidence and functional consequences of hMLH1 promoter hypermethylation in colorectal carcinomaIPMNs with co-occurring invasive cancers: neighbours but not always relativesLe 2015: PD-1 blockade works in tumours with mismatch-repair deficiency, whatever the organLe 2017: mismatch-repair deficiency predicts response to PD-1 blockade across twelve tumour types, leading to the first tissue-agnostic drug approvalLimited heterogeneity of known driver gene mutations among the metastases of individual patients with pancreatic cancerManagement of patients with increased risk for familial pancreatic cancer: updated recommendations from the International Cancer of the Pancreas Screening (CAPS) ConsortiumPancreatic intraepithelial neoplasia: a new nomenclature and classification system for pancreatic duct lesionsPardoll 2012: the blockade of immune checkpoints in cancer immunotherapyPrecancerous neoplastic cells can move through the pancreatic ductal systemPresence of somatic mutations in most early-stage pancreatic intraepithelial neoplasiaRecurrent GNAS mutations define an unexpected pathway for pancreatic cyst developmentRESTORE: bipolar androgen therapy after progression on enzalutamide in metastatic castration-resistant prostate cancerRisk of Neoplastic Progression in Individuals at High Risk for Pancreatic Cancer Undergoing Long-term SurveillanceThe molecular evolution of acquired resistance to targeted EGFR blockade in colorectal cancersThe Multicenter Cancer of Pancreas Screening Study: Impact on Stage and SurvivalThe tumour microenvironment in pancreatic cancer: clinical challenges and opportunitiesTRANSFORMER: bipolar androgen therapy versus enzalutamide in asymptomatic metastatic castration-resistant prostate cancerVogelstein, Lane and Levine 2000: surfing the p53 networkWhole genome sequencing defines the genetic heterogeneity of familial pancreatic cancerWhole-exome sequencing of neoplastic cysts of the pancreas reveals recurrent mutations in components of ubiquitin-dependent pathways
Open-source projects
All open source in oncology →Open-source projects that this organisation maintains, from OnCo's own catalogue: licence and last activity as the repository reported them on the day of the fetch. Listing is not endorsement; check the licence before reuse and the validation before clinical use.
A modular variant annotation platform with a store of annotators, including cancer-specific ones, and a browser-based results viewer.
162 starslast push 2026-09-21Johns Hopkins Hospital / Sidney Kimmel Comprehensive Cancer CenterRepositoryCode behind the DELFI cell-free DNA fragmentation approach to cancer detection, from the Velculescu lab at Johns Hopkins.
80 starslast push 2021-06-04Johns Hopkins Hospital / Sidney Kimmel Comprehensive Cancer CenterRepositoryClassifies genes as oncogenes or tumour suppressors from their mutation patterns.
50 starslast push 2026-09-02Johns Hopkins Hospital / Sidney Kimmel Comprehensive Cancer CenterRepositoryPredicts driver missense mutations, cancer type by cancer type, from the Karchin lab.
12 starslast push 2026-09-02Johns Hopkins Hospital / Sidney Kimmel Comprehensive Cancer CenterRepository